
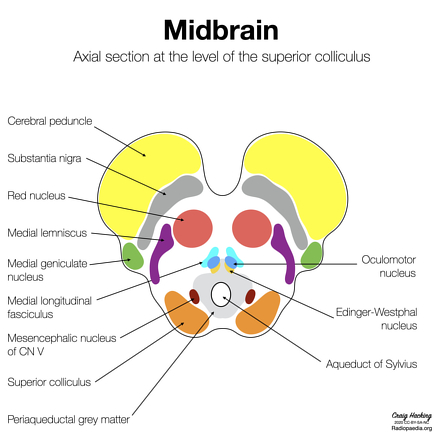
The limbic system is an old, loose label for deep brain structures, such as the amygdala, hypothalamus and hippocampus, that tag what matters, hold its context and set the body’s fast reactions in motion. The prefrontal cortex puts those reactions in context, names them and can quiet them, but stress weakens it quickly. Felt emotion comes from these systems working together, not from one emotional center.
This piece keeps the frame of the talk it grew out of: it is about how these systems feel, not only where they sit. My argument is that you cannot feel your amygdala, but you can learn to feel the difference between two kinds of experience. Prefrontal narration is verbal, sequential and open to revision. Subcortical alarm arrives in the body first and does not take arguments. Once a person can tell those apart from the inside, bottom-up therapy stops seeming mysterious. When alarm is running the show, more narration rarely settles it, and working with the body, attention and new experience is often a better place to start. The right kind of words, naming rather than arguing, help too.
What the “limbic system” actually is
The phrase has a history, and the history explains the confusion. In 1937 the neuroanatomist James Papez published “A Proposed Mechanism of Emotion,” which described a loop through the hypothalamus, thalamus, cingulate cortex and hippocampus.1 In 1952 Paul MacLean, building on Papez, wrote about the “limbic system,” which he also called the visceral brain.2 MacLean later folded it into his triune brain model, set out in full in a 1990 book. That model pictured a reptilian core, a paleomammalian limbic layer and a neomammalian cortex stacked on top of one another like geological strata.3
The earlier version of this post repeated that picture. It called the subcortical brain the oldest part of the brain and our link to reptilian ancestry. Neurobiologists set that model aside long ago. Joseph Cesario, David Johnson and Heather Eisthen were blunt about it in a 2020 paper titled “Your Brain Is Not an Onion With a Tiny Reptile Inside.” The belief that newer structures were laid over older ones as vertebrates evolved, they write, “has long been discredited among neurobiologists.”4 Living reptiles are our evolutionary cousins, not our ancestors, and their brains are not a fossil layer buried inside ours. Some reptiles do have a real light-sensing “third eye,” the parietal eye, and what it can and cannot tell us about trauma and intuition is the subject of our post on whether our reptile ancestors had a literal third eye.
Emotion does not live in one layer, either. A meta-analysis of human neuroimaging studies by Kristen Lindquist, Lisa Feldman Barrett and colleagues found little evidence that discrete emotions such as fear, anger or sadness map consistently onto specific regions. Emotional states instead recruited interacting networks that also carry out ordinary, non-emotional work.5 “Limbic system” is best read as shorthand for a set of deep and midline structures, including the amygdala, hypothalamus, hippocampus and parts of the cingulate cortex, that do a great deal of the work of detecting what matters and mobilizing the body. It is not an emotion organ, and the prefrontal cortex is not a thinking organ sitting on top of it.
What the prefrontal cortex does with emotion
The original post said that the old ice-pick lobotomies removed the prefrontal cortex, dulling personality while leaving basic functions intact. Neither half holds up. The Portuguese neurologist Egas Moniz and the neurosurgeon Almeida Lima performed the first prefrontal leucotomy in Lisbon in 1935.6,7 The operation did not remove cortex. It cut the white-matter connections between the prefrontal cortex and the thalamus, first with alcohol injections and then with an instrument called a leucotome. Moniz reported that his patients were calmer and more manageable, and that their emotional responses were blunted.6 He received the Nobel Prize in 1949, an award that remains controversial.7
In 1946 the American neurologist Walter Freeman introduced the transorbital “ice pick” lobotomy, and neurosurgeons were quick to criticize it.8 Freeman drove an ice-pick-like instrument through the roof of the eye socket into the base of the frontal lobes, often under local anesthesia or with the patient sedated after electroconvulsive shock.6 He performed more than 3,000 prefrontal and transorbital lobotomies before poor outcomes, regulatory scrutiny and the arrival of antipsychotic drugs pushed the operation to the margins.9
The lesson for this article runs opposite to the one the original drew. Lobotomy did not show that personality lives in the prefrontal cortex. If it showed anything, it was that cutting the prefrontal cortex off from deeper structures can flatten emotional life. In the same era, physicians linked damage to or removal of the frontal lobes, from injuries and from tumor surgery, with distractibility, apathy, lack of initiative, loss of restraint and social disinhibition.6 Feeling depends on the traffic between levels.
With the connections intact, the prefrontal cortex does at least three things with emotion. It reinterprets. When people deliberately change how they see an upsetting stimulus, usually a picture, a strategy called cognitive reappraisal, a meta-analysis of 48 imaging studies found consistent activation in cognitive control regions of the prefrontal and parietal cortex, but not in the ventromedial prefrontal cortex, and reduced activity in the amygdala on both sides. The authors read this as control regions changing the meaning of the stimulus, with the new meaning quieting the amygdala.10
It also remembers safety. When a learned fear is extinguished, the ventromedial prefrontal cortex appears to help hold on to the new learning. In a human study by Elizabeth Phelps and colleagues, activity in that region was linked to how well extinction held up at a delayed test, while amygdala activity tracked the fear response itself.11
And it takes part in telling the story, though the storyteller is not the prefrontal cortex alone. From decades of split-brain research, Michael Gazzaniga described a left-hemisphere “interpreter” that builds theories about why we act and keeps up our sense of being in charge, even though much of what we do is set in motion before we are aware of it.12 We look at what that means for depth psychology in our piece on Michael Gazzaniga and the interpreter. The original also equated the prefrontal cortex with Freud’s ego. That is a metaphor, and a loose one, not anatomy.
How narration and alarm feel from the inside
Phenomenology, as Maurice Merleau-Ponty practiced it in Phenomenology of Perception (1945), starts by describing experience as it is lived before explaining it, and treats that lived experience as bodily from the start.13 Applied here, the useful move is to stop asking where an emotion is located and start noticing what kind of experience it is.
Narration is made of words or something close to them. It runs in sequence. It can hold two views at once, argue with itself and notice when it is wrong. Watching a film, narration is the voice that says, “That’s clever. The director is borrowing an older tradition and subverting it.” You can slow it down, and it usually feels like you.
Alarm arrives in the body before it has a sentence: a jolt in the chest, heat in the face, narrowing vision, an urge to move, or a heaviness that makes moving hard. It comes all at once. It does not respond to reasons, and it often feels as if it is happening to you rather than being done by you. When narration shows up afterward, it tends to justify the alarm rather than inform it.
The science supports the distinction, though not a simple map of it. Joseph LeDoux, whose fear-conditioning research helped establish the amygdala’s role in threat, has argued that the field lost ground by treating these as one thing. In a 2016 paper with Daniel Pine, he separates the circuits that produce defensive behavior and bodily change from those that produce the conscious feeling a person reports as fear or anxiety, and argues that blurring the two has held back treatment.14 The affective neuroscientist Jaak Panksepp took a different view. Electrical stimulation of deep subcortical regions evokes strong emotional behavior across mammals and comparable feelings in humans, which he read as evidence that raw feeling begins below the cortex.15 That debate is not settled, and LeDoux’s split has critics of its own. Michael Fanselow and Zachary Pennington argue that fear is one integrated response generated by shared upstream circuits, while granting that its bodily and felt components can be changed and studied separately.16 The clinical point survives the argument: the body’s fast response and the feeling a person can put into words do not always move together, and that gap is what a client can learn to notice.
A third finding complicates any one-switch picture. Three rare patients with damage to the amygdala on both sides felt fear and had panic attacks after inhaling a gas mixture containing 35 percent carbon dioxide. The authors concluded that the amygdala is not required for fear and panic, at least when the threat comes from inside the body.17 The body itself is a source of information. Interoception, the nervous system’s sensing of the body’s internal state, is carried by an afferent system that A. D. Craig mapped in primates and humans and proposed might provide a foundation for subjective feeling.18 A 2018 consensus review lists disrupted interoception as a component of anxiety, mood, eating, addictive and somatic symptom disorders, while warning that conceptual and measurement problems still limit how widely the idea can be applied.19
The original said the subcortical brain decides whether to “mate, flee, or freeze.” A better-grounded description, from a clinical review, is the defense cascade: arousal first, then fight or flight; freezing as fight or flight put on hold; and, when escape seems impossible, tonic or collapsed immobility. Kasia Kozlowska and colleagues tie each response to patterns in the amygdala, hypothalamus, periaqueductal gray and the sympathetic and vagal nuclei. They note that humans, unlike most animals, can stay locked in the pattern long after the danger has passed.20 We make a related case about the brain stem in why logic alone can’t heal trauma.
Not every automatic reaction is an emotional one. The knee-jerk the original used as an example is a muscle stretch reflex routed through the spinal cord at the L2 to L4 segments. Descending pathways from the brain modulate it, which is one reason neurologists test it, but no part of the emotional brain decides to kick.21
Why insight goes offline under stress
Most people in therapy know some version of this. What they understood clearly on Tuesday is gone during Thursday’s argument. Amy Arnsten’s review of stress signaling explains part of why. Even mild acute stress, if it is uncontrollable, can cause a rapid loss of prefrontal abilities, while emotional associations in the amygdala and motor habits in the striatum hold up or grow stronger. In her words, stress “switches the control of behaviour and emotion to more primitive brain circuits.”22 In context, “primitive” refers to the amygdala and the striatum’s habit circuits, not to a reptile brain. The basal ganglia, which the original lumped into a deep emotional system, appear in this account mainly as the machinery of habit. Prolonged stress goes further and changes the structure of prefrontal dendrites.22
Imaging studies of anxiety show a similar tilt. A 2007 meta-analysis by Amit Etkin and Tor Wager found more amygdala and insula activity in PTSD, social anxiety disorder and specific phobia than in comparison groups. Only PTSD also showed reduced activity in the ventromedial prefrontal cortex and the dorsal and rostral anterior cingulate, regions linked to regulating emotion.23
Too little prefrontal control is not the only way this goes wrong. Ruth Lanius and colleagues describe a dissociative subtype of PTSD in which the problem runs the other way. Midline prefrontal regions over-inhibit limbic regions, and the person goes numb, distant or unreal instead of flooded. The two patterns can alternate in the same person, and the authors call for assessing people with PTSD for dissociative symptoms.24 From the inside, over-control can feel like narration with nobody home. This is one reason “more top-down control” is not the goal of therapy, and why dissociation therapy needs its own pacing.
What this looks like in therapy
The first task is usually noticing. A therapist may ask someone to track what happens in the body while telling a hard story, and to say when it changes: the voice speeds up, the chest tightens, the story starts looping. With practice, people learn to catch the moment narration hands off to alarm. That moment is useful, because it marks where explanation alone stops working.
The original made a point worth keeping. A child who learns that being vulnerable gets them hurt does not store that lesson as a belief they can debate. It is stored as a readiness to brace. Years later, the adult may know perfectly well that a partner is safe and still tense up when they reach for closeness. Telling that adult to think differently aims at the wrong level.
Words still matter when they are the right kind. In a 2007 brain-imaging study led by Matthew Lieberman, naming the emotion in a picture reduced the amygdala’s response compared with other ways of processing it, and increased activity in the right ventrolateral prefrontal cortex.25 Labeling a feeling may not feel like regulating it, yet it produces many of the same effects as deliberate regulation, which is why Jared Torre and Lieberman describe it as implicit emotion regulation.26 A 2012 experiment moved the idea closer to the clinic. Eighty-eight spider-fearful volunteers, recruited from a university course and the community, were repeatedly exposed to a live tarantula. Those told to put their feelings into words, with sentences such as “I feel anxious the disgusting tarantula will jump on me,” showed lower skin conductance a week later, with a different spider in a different setting, than those who reappraised, distracted themselves or did exposure alone. Their self-reported fear did not differ.27 In that one study, naming the alarm did more for the body’s measured response than reasoning about it, though not for how afraid people said they felt.
New learning tends to sit beside old learning rather than erase it. Mark Bouton’s review of extinction research, much of it from animal studies, concludes that extinction does not destroy the original learning. It adds new learning that is especially dependent on context.28 That is one reason calm in the therapy room can fail to carry over to the drive home, and why good therapy practices the new response in more than one setting.
Some researchers think therapy can do more than add a competing memory. Richard Lane and colleagues proposed in 2015 that change across many therapies comes from reactivating an old emotional memory, bringing in a new emotional experience while that memory is open to updating, a process called reconsolidation, and then practicing the new response in varied contexts.29 It is a proposal built on emerging laboratory evidence, not a settled account of how therapy works. Bruce Ecker, Robin Ticic and Laurel Hulley put the same idea at the center of their clinical approach,30 which we cover in our piece on Coherence Therapy and memory reconsolidation.
Bottom-up therapies work at the level of alarm through sensation, posture, breath and attention. The evidence is real but early. A 2021 scoping review of Somatic Experiencing, which included 16 studies, found preliminary evidence of positive effects on PTSD symptoms, mixed study quality and a clear need for unbiased randomized trials.31 The first randomized trial, with 63 participants, found large reductions in PTSD symptoms compared with a waitlist, a weaker comparison than an active treatment.32 In a single trial of 64 women with chronic, treatment-resistant PTSD, 16 of 31 in a ten-week trauma-informed yoga class no longer met criteria for PTSD at the end, against 6 of 29 in a health-education control.33 Mindfulness research broadly supports benefits for health and emotional life, but a major review concluded that the neural mechanisms remain unclear and that more rigorous studies are needed.34 The honest summary: these methods make sense given what we know about alarm and narration, and some have encouraging trials, but none is established well enough to be sold as a proven treatment. That is how we approach somatic therapy in Birmingham.
Where the two-system picture breaks down
Narration versus alarm is a clinical tool, not a brain scan, and it has limits.
You cannot feel your amygdala or your prefrontal cortex. What you feel are states that these and many other regions produce together.5 Calling a sensation “my amygdala” can be a helpful way to step back from it, but it is a figure of speech.
The prefrontal cortex is not only a brake. In one leading theory of consciousness, it is also part of how information becomes conscious at all. Stanislas Dehaene and Jean-Pierre Changeux describe information becoming reportable when it “ignites” a large prefronto-parietal network,35 work we cover in our profile of Stanislas Dehaene and conscious ignition. LeDoux and Pine point to evidence that defensive responses can run without that kind of awareness.14
Language is not the enemy. A system made only of words can narrate fluently with no alarm and no body beneath it, which is part of our argument for why consciousness won’t emerge from large language models. People need both levels, talking to each other.
Brain-based claims also outrun their data easily. Measures of brain activity are real but coarser than these labels suggest, and our review of what the research says about qEEG and neuromodulation shows how wide that gap can get.
If you know the moment when everything you understand drops out and your body takes over, that is a reasonable place to start therapy, not a sign you are doing it wrong. Taproot Therapy Collective works with that moment in Hoover, minutes from Birmingham, and in teletherapy across Alabama. You can reach us through our contact page with questions.
References
- Papez, J. W. (1937). A proposed mechanism of emotion. Archives of Neurology and Psychiatry, 38(4), 725–743. https://doi.org/10.1001/archneurpsyc.1937.02260220069003
- MacLean, P. D. (1952). Some psychiatric implications of physiological studies on frontotemporal portion of limbic system (visceral brain). Electroencephalography and Clinical Neurophysiology, 4(4), 407–418. https://doi.org/10.1016/0013-4694(52)90073-4
- MacLean, P. D. (1990). The triune brain in evolution: Role in paleocerebral functions. Plenum Press.
- Cesario, J., Johnson, D. J., & Eisthen, H. L. (2020). Your brain is not an onion with a tiny reptile inside. Current Directions in Psychological Science, 29(3), 255–260. https://doi.org/10.1177/0963721420917687
- Lindquist, K. A., Wager, T. D., Kober, H., Bliss-Moreau, E., & Barrett, L. F. (2012). The brain basis of emotion: A meta-analytic review. Behavioral and Brain Sciences, 35(3), 121–143. https://doi.org/10.1017/S0140525X11000446
- Faria, M. A., Jr. (2013). Violence, mental illness, and the brain: A brief history of psychosurgery: Part 1. From trephination to lobotomy. Surgical Neurology International, 4, 49. https://doi.org/10.4103/2152-7806.110146
- Gross, D., & Schäfer, G. (2011). Egas Moniz (1874–1955) and the “invention” of modern psychosurgery: A historical and ethical reanalysis under special consideration of Portuguese original sources. Neurosurgical Focus, 30(2), E8. https://doi.org/10.3171/2010.10.FOCUS10214
- Collins, B. M., & Stam, H. J. (2015). Freeman’s transorbital lobotomy as an anomaly: A material culture examination of surgical instruments and operative spaces. History of Psychology, 18(2), 119–131. https://doi.org/10.1037/a0039061
- Caruso, J. P., & Sheehan, J. P. (2017). Psychosurgery, ethics, and media: A history of Walter Freeman and the lobotomy. Neurosurgical Focus, 43(3), E6. https://doi.org/10.3171/2017.6.FOCUS17257
- Buhle, J. T., Silvers, J. A., Wager, T. D., Lopez, R., Onyemekwu, C., Kober, H., Weber, J., & Ochsner, K. N. (2014). Cognitive reappraisal of emotion: A meta-analysis of human neuroimaging studies. Cerebral Cortex, 24(11), 2981–2990. https://doi.org/10.1093/cercor/bht154
- Phelps, E. A., Delgado, M. R., Nearing, K. I., & LeDoux, J. E. (2004). Extinction learning in humans: Role of the amygdala and vmPFC. Neuron, 43(6), 897–905. https://doi.org/10.1016/j.neuron.2004.08.042
- Gazzaniga, M. S. (2000). Cerebral specialization and interhemispheric communication: Does the corpus callosum enable the human condition? Brain, 123(7), 1293–1326. https://doi.org/10.1093/brain/123.7.1293
- Merleau-Ponty, M. (2012). Phenomenology of perception (D. A. Landes, Trans.). Routledge. (Original work published 1945) https://doi.org/10.4324/9780203720714
- LeDoux, J. E., & Pine, D. S. (2016). Using neuroscience to help understand fear and anxiety: A two-system framework. American Journal of Psychiatry, 173(11), 1083–1093. https://doi.org/10.1176/appi.ajp.2016.16030353
- Panksepp, J. (2011). Cross-species affective neuroscience decoding of the primal affective experiences of humans and related animals. PLoS ONE, 6(9), Article e21236. https://doi.org/10.1371/journal.pone.0021236
- Fanselow, M. S., & Pennington, Z. T. (2018). A return to the psychiatric dark ages with a two-system framework for fear. Behaviour Research and Therapy, 100, 24–29. https://doi.org/10.1016/j.brat.2017.10.012
- Feinstein, J. S., Buzza, C., Hurlemann, R., Follmer, R. L., Dahdaleh, N. S., Coryell, W. H., Welsh, M. J., Tranel, D., & Wemmie, J. A. (2013). Fear and panic in humans with bilateral amygdala damage. Nature Neuroscience, 16(3), 270–272. https://doi.org/10.1038/nn.3323
- Craig, A. D. (2002). How do you feel? Interoception: The sense of the physiological condition of the body. Nature Reviews Neuroscience, 3(8), 655–666. https://doi.org/10.1038/nrn894
- Khalsa, S. S., Adolphs, R., Cameron, O. G., Critchley, H. D., Davenport, P. W., Feinstein, J. S., Feusner, J. D., Garfinkel, S. N., Lane, R. D., Mehling, W. E., Meuret, A. E., Nemeroff, C. B., Oppenheimer, S., Petzschner, F. H., Pollatos, O., Rhudy, J. L., Schramm, L. P., Simmons, W. K., Stein, M. B., … Paulus, M. P. (2018). Interoception and mental health: A roadmap. Biological Psychiatry: Cognitive Neuroscience and Neuroimaging, 3(6), 501–513. https://doi.org/10.1016/j.bpsc.2017.12.004
- Kozlowska, K., Walker, P., McLean, L., & Carrive, P. (2015). Fear and the defense cascade: Clinical implications and management. Harvard Review of Psychiatry, 23(4), 263–287. https://doi.org/10.1097/HRP.0000000000000065
- Rodriguez-Beato, F. Y., & De Jesus, O. (2023). Physiology, deep tendon reflexes. In StatPearls. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK562238/
- Arnsten, A. F. T. (2009). Stress signalling pathways that impair prefrontal cortex structure and function. Nature Reviews Neuroscience, 10(6), 410–422. https://doi.org/10.1038/nrn2648
- Etkin, A., & Wager, T. D. (2007). Functional neuroimaging of anxiety: A meta-analysis of emotional processing in PTSD, social anxiety disorder, and specific phobia. American Journal of Psychiatry, 164(10), 1476–1488. https://doi.org/10.1176/appi.ajp.2007.07030504
- Lanius, R. A., Vermetten, E., Loewenstein, R. J., Brand, B., Schmahl, C., Bremner, J. D., & Spiegel, D. (2010). Emotion modulation in PTSD: Clinical and neurobiological evidence for a dissociative subtype. American Journal of Psychiatry, 167(6), 640–647. https://doi.org/10.1176/appi.ajp.2009.09081168
- Lieberman, M. D., Eisenberger, N. I., Crockett, M. J., Tom, S. M., Pfeifer, J. H., & Way, B. M. (2007). Putting feelings into words: Affect labeling disrupts amygdala activity in response to affective stimuli. Psychological Science, 18(5), 421–428. https://doi.org/10.1111/j.1467-9280.2007.01916.x
- Torre, J. B., & Lieberman, M. D. (2018). Putting feelings into words: Affect labeling as implicit emotion regulation. Emotion Review, 10(2), 116–124. https://doi.org/10.1177/1754073917742706
- Kircanski, K., Lieberman, M. D., & Craske, M. G. (2012). Feelings into words: Contributions of language to exposure therapy. Psychological Science, 23(10), 1086–1091. https://doi.org/10.1177/0956797612443830
- Bouton, M. E. (2004). Context and behavioral processes in extinction. Learning & Memory, 11(5), 485–494. https://doi.org/10.1101/lm.78804
- Lane, R. D., Ryan, L., Nadel, L., & Greenberg, L. (2015). Memory reconsolidation, emotional arousal, and the process of change in psychotherapy: New insights from brain science. Behavioral and Brain Sciences, 38, Article e1. https://doi.org/10.1017/S0140525X14000041
- Ecker, B., Ticic, R., & Hulley, L. (2012). Unlocking the emotional brain: Eliminating symptoms at their roots using memory reconsolidation. Routledge. https://doi.org/10.4324/9780203804377
- Kuhfuß, M., Maldei, T., Hetmanek, A., & Baumann, N. (2021). Somatic experiencing: Effectiveness and key factors of a body-oriented trauma therapy: A scoping literature review. European Journal of Psychotraumatology, 12(1), Article 1929023. https://doi.org/10.1080/20008198.2021.1929023
- Brom, D., Stokar, Y., Lawi, C., Nuriel-Porat, V., Ziv, Y., Lerner, K., & Ross, G. (2017). Somatic experiencing for posttraumatic stress disorder: A randomized controlled outcome study. Journal of Traumatic Stress, 30(3), 304–312. https://doi.org/10.1002/jts.22189
- van der Kolk, B. A., Stone, L., West, J., Rhodes, A., Emerson, D., Suvak, M., & Spinazzola, J. (2014). Yoga as an adjunctive treatment for posttraumatic stress disorder: A randomized controlled trial. Journal of Clinical Psychiatry, 75(6), e559–e565. https://doi.org/10.4088/JCP.13m08561
- Tang, Y.-Y., Hölzel, B. K., & Posner, M. I. (2015). The neuroscience of mindfulness meditation. Nature Reviews Neuroscience, 16(4), 213–225. https://doi.org/10.1038/nrn3916
- Dehaene, S., & Changeux, J.-P. (2011). Experimental and theoretical approaches to conscious processing. Neuron, 70(2), 200–227. https://doi.org/10.1016/j.neuron.2011.03.018


















0 Comments