
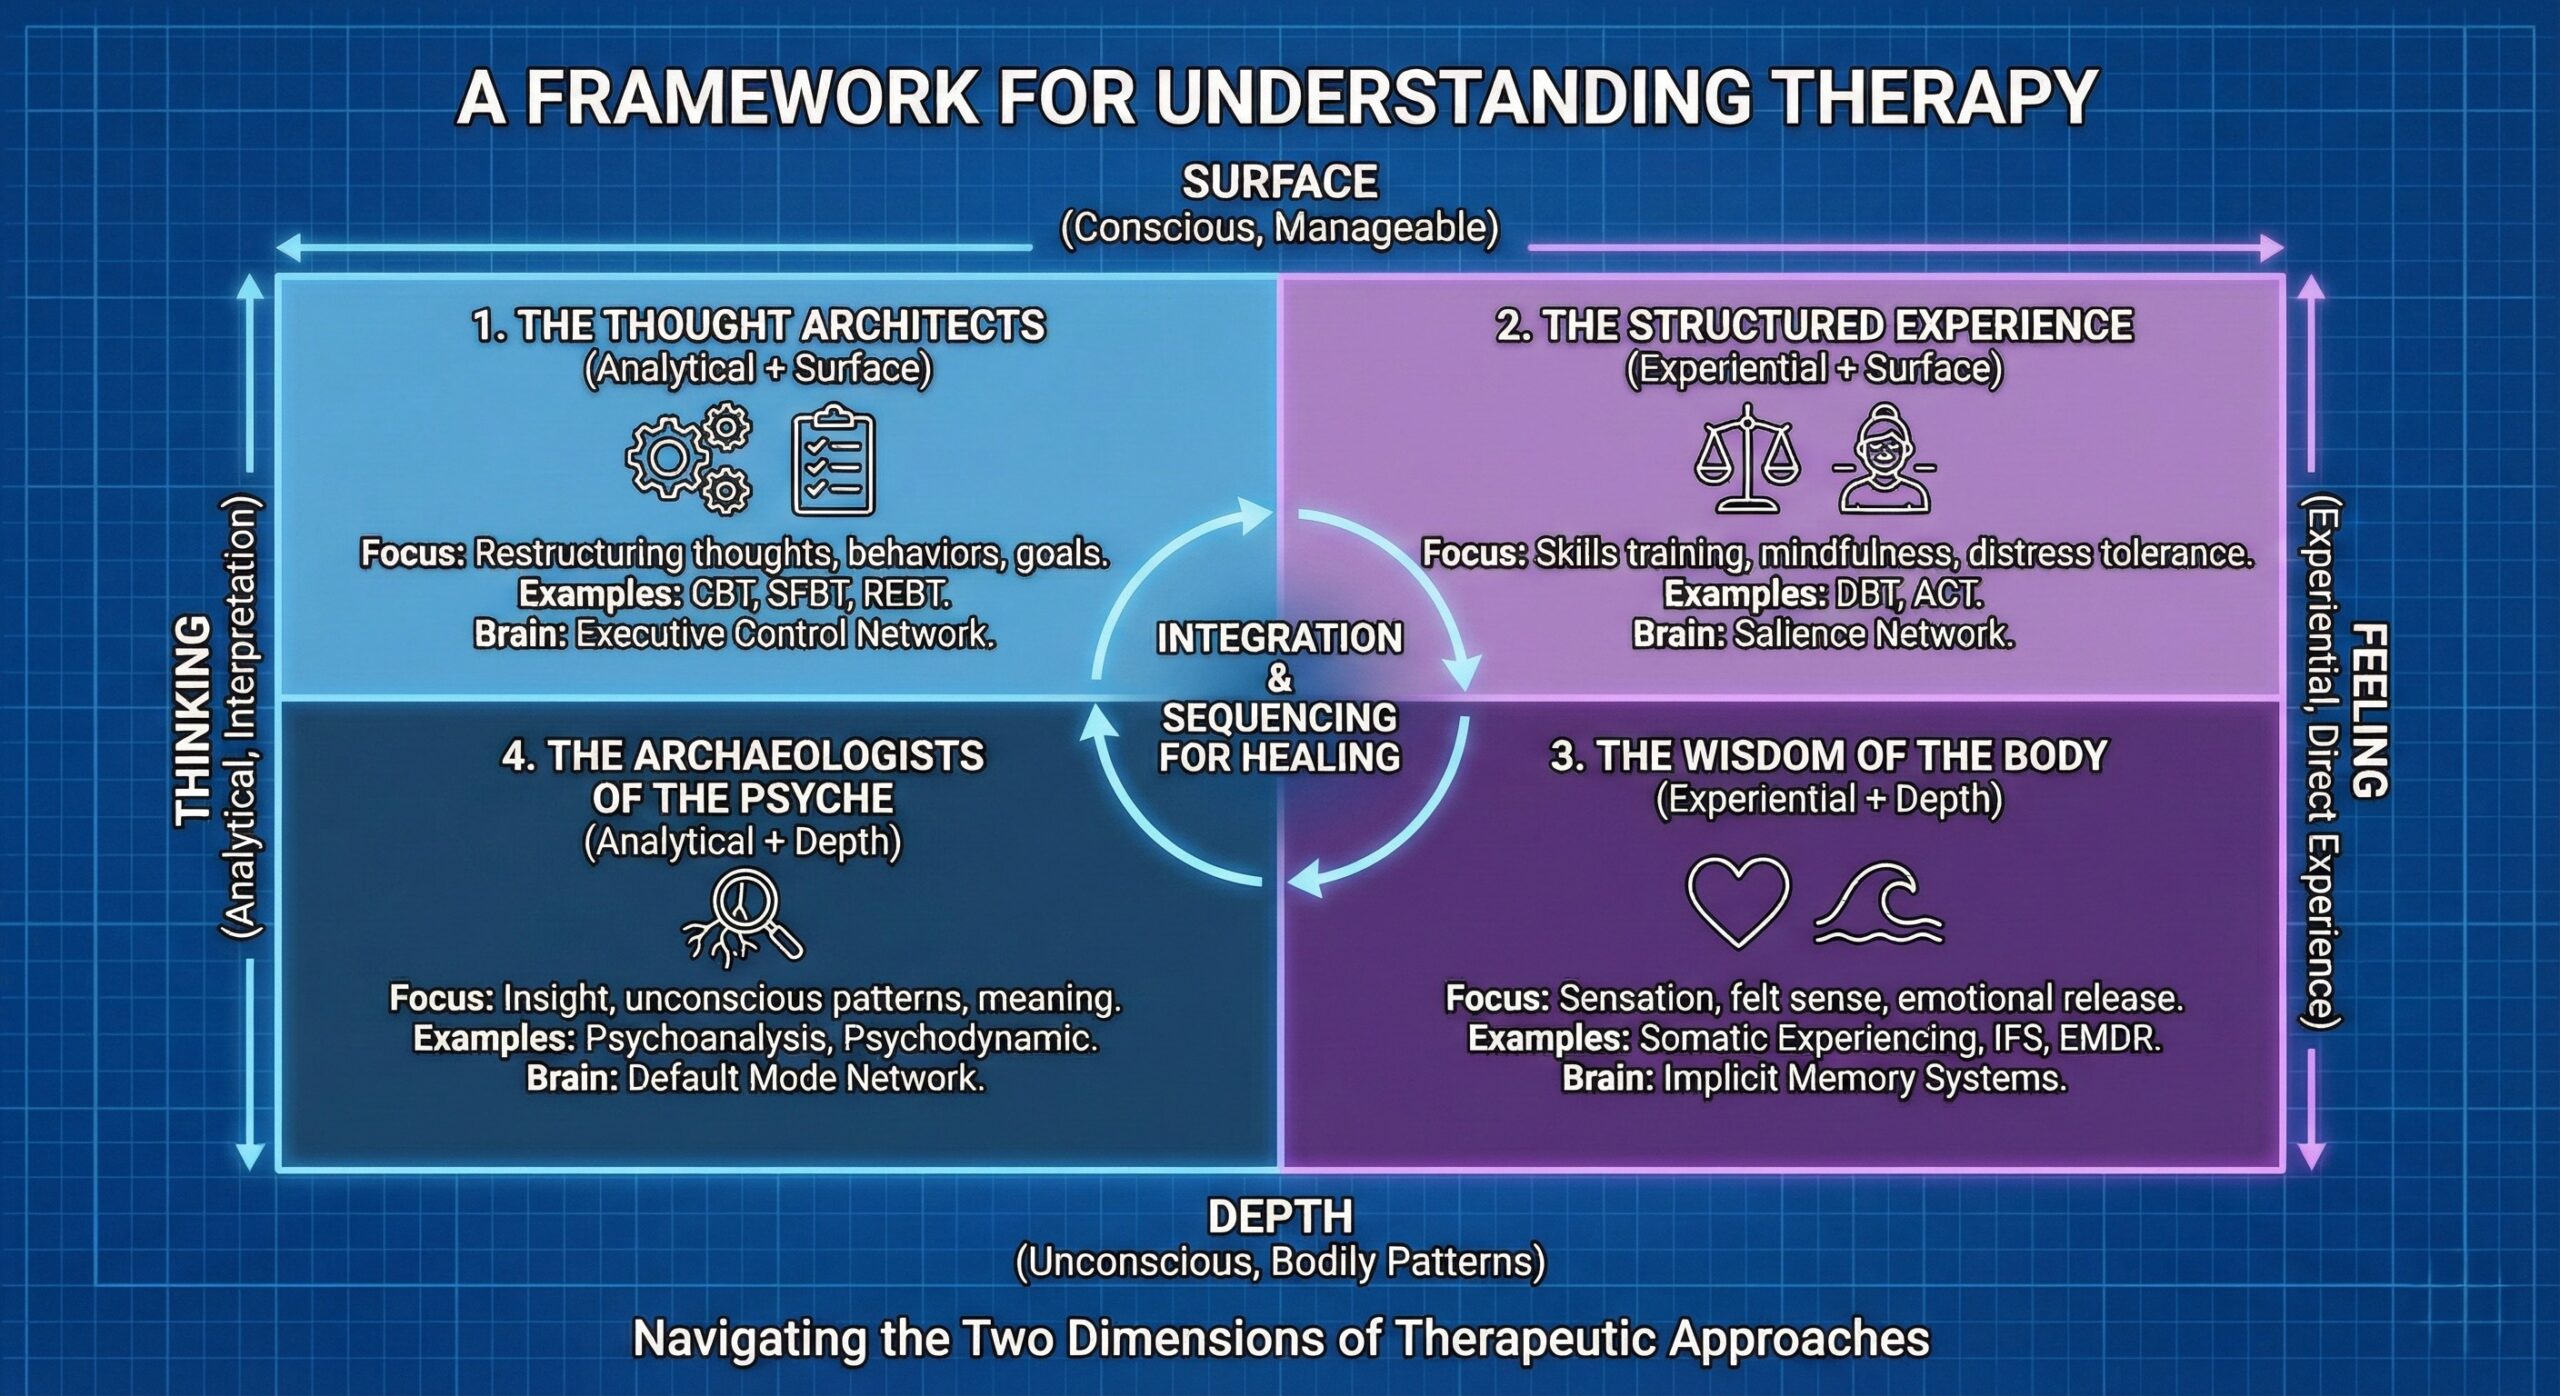
Most types of therapy fall into five families: cognitive-behavioral therapies (CBT, exposure, behavioral activation), skills and acceptance therapies (DBT, ACT), trauma-processing therapies (cognitive processing therapy, prolonged exposure, EMDR), body-based and parts-based therapies (Somatic Experiencing, Brainspotting, IFS), and psychodynamic or depth therapies (psychoanalytic, Jungian, existential). They differ mainly in where they start and which stage of change they serve.
The argument of this page is that the brand name matters less than two questions. Does the therapy enter top-down, through words, beliefs and meaning, or bottom-up, through sensation, emotion and action? And is it built to stabilize, to process, or to integrate? Matching those answers to the person, and changing them as the person changes, is how you avoid years in the wrong room. The research adds a correction the earlier version of this page missed: the best-supported treatments already cross the top-down and bottom-up line, and among established therapies the relationship and your own preferences predict outcome at least as strongly as the choice of method.
Two questions that sort almost every therapy
There are hundreds of named psychotherapies, and our dictionary of psychotherapy models is long for a reason. Underneath the acronyms, the first sorting question is direction. Top-down approaches start with language and thought: you name a belief, examine it, test it, and expect the change to travel down into feeling and behavior. Bottom-up approaches start with a body sensation, an impulse to move, an emotion or the felt image of a memory, and expect the change to travel up into new meaning. Pat Ogden, who developed Sensorimotor Psychotherapy, made this distinction central to Trauma and the Body (2006), written with Kekuni Minton and Clare Pain, and the book argues for combining the two directions rather than choosing one.1
The distinction is not only a clinician’s metaphor. In a 2012 experiment, Kateri McRae, James Gross and colleagues produced negative emotion in two ways: bottom-up, from pictures whose content is aversive in itself, and top-down, from the person’s own negative evaluation of what they saw. Cognitive reappraisal, a close relative of the cognitive restructuring taught in CBT, reduced reported distress more for the top-down emotions. Reappraising the bottom-up emotions produced a paradoxical increase in amygdala activity.2 One laboratory study does not settle clinical practice, but it fits what therapists see every week: arguing with a feeling that did not start as a thought often goes badly.
The second question is phase. In Trauma and Recovery (1992), Judith Herman described recovery from trauma in three stages: establishing safety, remembrance and mourning, and reconnection with ordinary life, and she wrote that no course of recovery follows them in a straight line.3 Our profile of Judith Herman and her stage model of recovery covers where that idea came from. Most therapies are strongest in one phase. Skills therapies stabilize. Trauma-focused therapies process. Depth therapies help a person integrate what happened into a life story that makes sense.
Direction and phase together give the map we use at Taproot. It is a clinical heuristic, not a research taxonomy. The earlier version of this page went further and assigned each quadrant of the map to a specific brain network. The evidence below does not support that, and it shows that the boundaries leak in useful ways.
The main types of therapy and what each is built to do
Cognitive and behavioral therapies
Aaron Beck’s 1963 paper on thinking and depression described the recurring, distorted themes in depressed patients’ thoughts, and it became a starting point for cognitive therapy.4 CBT is now a family that includes cognitive restructuring, behavioral activation, exposure and problem solving. Sessions usually have an agenda, there is practice between sessions, and progress is measured. A 2012 review of 106 meta-analyses by Stefan Hofmann and colleagues found the strongest support for CBT in anxiety disorders, somatoform disorders, bulimia, anger problems and general stress.5
CBT is not purely top-down. Exposure, the behavioral core of CBT for anxiety and PTSD, works through new learning in the fear system itself. Michelle Craske’s inhibitory learning account describes exposure as building a new association that competes with the old fear, rather than erasing that fear or simply disproving a belief, and one of the strategies her team recommends is putting the feeling into words while it is present.6 The earlier version of this page put CBT in a “thinking” box whose work does not always reach the body, and said purely cognitive approaches leave some trauma responses intact. The PTSD guidelines discussed below rank exposure-based and cognitive-processing therapies first, which is hard to square with that claim.
Skills and acceptance therapies
Marsha Linehan developed dialectical behavior therapy out of early attempts to apply standard behavior therapy to highly suicidal clients, by trial and error and mostly from clinical experience. DBT combines individual therapy, group skills training, phone coaching and a consultation team for the therapists.7 Her 1993 treatment manual was written for borderline personality disorder.8 The 2020 Cochrane review of psychological therapies for that diagnosis found benefits for therapies tailored to it compared with usual care, including effects of DBT on severity, self-harm and day-to-day functioning, though the reviewers rated all of the DBT findings as low-quality evidence.9 Acceptance and commitment therapy belongs in the same broad family. The skills are taught in words and practiced in the body, which is why these therapies sit near the middle of the map.
Trauma-focused processing therapies
Cognitive processing therapy works top-down on the beliefs a trauma left behind, such as “it was my fault” or “no one can be trusted.” Prolonged exposure asks the person to revisit the memory and approach what they have been avoiding, a bottom-up route that relies on extinction learning. EMDR pairs recall of the memory with sets of bilateral eye movements. A 2020 meta-analysis of 76 EMDR trials by Pim Cuijpers and colleagues concluded that EMDR may be effective for PTSD in the short term but that study quality was too low for definite conclusions: only 4 of 27 studies had a low risk of bias, and the apparent advantage over other therapies disappeared in those better studies.10 We cover that debate in more depth in is EMDR evidence-based?, and the older history of eye-movement methods in the IS map and how eye movements became a system.
Body-based and parts-based therapies
Somatic Experiencing, developed by Peter Levine, treats post-traumatic symptoms by working with the internal body sensations and sense of position and movement linked to the traumatic experience. The first randomized trial, by Danny Brom and colleagues in 2017, compared 15 weekly sessions with a waitlist in 63 people with PTSD and found large effects on PTSD symptoms and moderate-to-large effects on depression.11 A 2021 scoping review called the evidence preliminary and the study quality mixed.12
Brainspotting, developed by David Grand, has the client hold their gaze on a point in the visual field linked to a felt body response while attending to what arises. The original version of this page said those points connect to the amygdala, hippocampus and orbitofrontal cortex. What exists is a 2013 paper by Frank Corrigan and Grand in Medical Hypotheses that sets out, as testable hypotheses, a visual pathway through the superior colliculi and a healing process located in the midbrain, including the periaqueductal gray.13 We know of no study that has confirmed them. The outcome research is small: one 2022 study gave 40 psychologists and physicians single 40-minute sessions of EMDR, Brainspotting and body-scan meditation for distressing memories and found reductions with all three, in a non-clinical sample.14 Internal Family Systems, which treats the mind as a system of parts, has a similar evidence profile. The PTSD study usually cited for it is an uncontrolled pilot with 17 adults who had survived multiple childhood traumas.15 We offer all three through our somatic therapy services for the Birmingham area, and you should know that their evidence is promising but thin.
Psychodynamic, Jungian and existential therapies
These therapies use interpretation, which is top-down, to reach material that sits outside awareness, and they treat the relationship with the therapist as part of the evidence. Sessions are less structured and treatment is often longer. Jonathan Shedler’s 2010 review in American Psychologist found effect sizes for psychodynamic therapy as large as those for therapies promoted as evidence-based, with gains that tended to hold or grow after treatment ended.16 Jungian analysis and existential therapy have a much smaller trial literature of their own. Their strength is the meaning-making work of Herman’s third stage, and they are a poor first choice for someone in acute crisis.
What research says about matching a person to a therapy
The honest starting point is that specific brands matter less than people expect. Bruce Wampold’s 1997 meta-analysis of direct comparisons between bona fide therapies found that the differences clustered near zero, a result summed up in its subtitle, “all must have prizes.”17 The therapeutic alliance, by contrast, predicts outcome reliably: a 2018 synthesis of 295 studies covering more than 30,000 patients found a correlation of about .28 between alliance and outcome, across treatment types.18
Your preferences count too. In a 2018 meta-analysis of 53 studies and more than 16,000 clients, people who got the kind of treatment they preferred were less likely to drop out (odds ratio 1.79) and had somewhat better outcomes (d = 0.28).19 The trial evidence is also narrower than lists of “evidence-based” therapies suggest. Drew Westen and colleagues argued in 2004 that the assumptions behind randomized trials fit some problems well, notably exposure for specific anxiety symptoms, but are badly violated for others.20
So where does personality come in? The earlier version of this page leaned on John Beebe’s eight-function model of psychological type and Naomi Quenk’s account of being “in the grip” of the inferior function under stress, and claimed that your growth edge is usually in the approach you avoid.21,22 These are useful clinical lenses, and our piece on Naomi Quenk and the inferior function explains them. They are not tested predictors of which therapy will work, and the Myers-Briggs instrument that grew from the same tradition has well-documented psychometric problems.23 The defensible version is smaller. A preference can be wisdom, and it can be a defense. The person who explains their panic fluently may be asking for more explanation when they need to feel the panic and find they survive it. The person flooded by feeling may want more catharsis when they need structure first. A good therapist says this out loud and decides with you, rather than overriding you.
What brain science can and cannot tell you
Vinod Menon’s triple network model groups much psychiatric research around three large brain systems: the default mode network, active during self-referential thought and mind-wandering; the central executive network, which supports goal-directed control; and the salience network, anchored in the anterior insula and dorsal anterior cingulate, which flags what deserves attention.24 Marcus Raichle’s group described the default mode in 2001.25 Lucina Uddin’s 2015 review covers the salience network and the insula.26 Michael Fox and colleagues reported in 2005 that default and task-related networks are anticorrelated at rest,27 although Kevin Murphy and colleagues later showed that a common preprocessing step, global signal regression, can produce such anticorrelations by itself, so that seesaw should be treated with caution.28
None of this shows that CBT works by strengthening the executive network, that DBT trains the salience network, or that analysis lives in the default mode network, as the earlier version claimed. Mapping therapies onto networks is a metaphor. The line “the insula doesn’t speak English” was a slogan, not a finding. Bud Craig’s influential account puts the anterior insula at the center of interoception and subjective feeling,29 but that does not put feeling beyond the reach of words. In Matthew Lieberman’s 2007 imaging study, simply labeling the emotion in a picture reduced the response of the amygdala and other limbic regions.30 Bessel van der Kolk’s The Body Keeps the Score (2014) popularized the idea that trauma is held in the body.31 The firmer version of that idea comes from memory research. Larry Squire’s work shows that the brain runs several memory systems, some open to conscious recall and some not,32 and Chris Brewin’s dual representation theory distinguishes flexible, contextual memories from inflexible, sensory-bound ones that drive flashbacks.33 We walk through those systems in how trauma is stored in different types of memory.
Depression shows why precision matters. The earlier page said rumination reflects an overactive default mode network. A 2015 meta-analytic review by J. Paul Hamilton, Ian Gotlib and colleagues found something more specific: increased connectivity between the default mode network and the subgenual prefrontal cortex, which often tracks rumination, without a reliable blood-flow abnormality in the default mode nodes themselves.34 The clinical lesson survives, in narrower form. Some states are poorly reached by more talk about the state.
PTSD: what the guidelines recommend, and where sequencing fits
The American Psychological Association’s PTSD guideline strongly recommends four psychotherapies: cognitive-behavioral therapy, cognitive processing therapy, cognitive therapy and prolonged exposure. It conditionally recommends brief eclectic psychotherapy, EMDR and narrative exposure therapy.35 The 2023 VA/DoD guideline recommends prolonged exposure, cognitive processing therapy or EMDR, and prefers these manualized psychotherapies to medication.36 The International Society for Traumatic Stress Studies guidelines released in 2018 gave their strongest rating to trauma-focused CBT, cognitive processing therapy, cognitive therapy, EMDR and prolonged exposure, while noting that dropout from trauma-focused treatment runs higher than from other therapies.37 None of these guidelines lists Somatic Experiencing, Brainspotting or IFS among its recommended treatments. The ISTSS review placed Somatic Experiencing among six approaches with “emerging evidence,” alongside acupuncture, neurofeedback and yoga, which is a step below a recommendation.38 Medication questions belong with a prescriber.
The earlier version of this page described a “hyperarousal subtype” and a “dissociative subtype” with opposite brain patterns, and suggested that hyperaroused clients may need cognitive tools first while dissociative clients may need gentle somatic activation. Part of that is real. The DSM-5-TR includes a dissociative specifier for PTSD.39 Ruth Lanius and colleagues proposed in 2010 that the common form of PTSD involves emotional undermodulation, with prefrontal regions failing to inhibit limbic areas, while the dissociative form involves overmodulation, with midline prefrontal regions over-inhibiting them.40 A 2007 meta-analysis by Amit Etkin and Tor Wager found reduced activity in the anterior cingulate and ventromedial prefrontal cortex specific to PTSD, alongside amygdala and insula overactivity shared with other anxiety disorders and seen less often in PTSD than in social anxiety or specific phobia.41 The treatment advice did not hold up. A 2020 meta-analysis of 21 trials and 1,714 patients found that dissociation before treatment did not predict how well people did in psychotherapy for PTSD.42 On current evidence, dissociation should be assessed and planned for, but it is not by itself a reason to withhold trauma-focused treatment.
The same tension runs through complex PTSD. In a 2011 ISTSS survey of 50 experts, 84 percent endorsed a phase-based or sequenced approach.43 In 2016, Ad de Jongh, Patricia Resick and 19 coauthors argued that no rigorous research shows a stabilization phase is necessary, and that requiring one may delay treatments people could benefit from.44 Our position sits between them. Stabilize enough to do the work, set a point at which you will review it, and do not let stabilization become the whole treatment.
Sequencing without stalling
For depression, the bottom-up starting point is often behavioral. A 2014 meta-analysis of 26 trials found behavioral activation clearly better than control conditions, though most of the trials were of low quality,45 and the COBRA trial in the United Kingdom found it no less effective than full CBT at 12 months, even when delivered by junior mental health workers.46 For persistent rumination, Ed Watkins’s rumination-focused CBT improved residual depression when added to usual care in a 42-person trial, though without an attention-control group.47 The earlier page claimed that insight-oriented therapy can make rumination worse. We could find no study showing that, and it is cut.
For trauma with heavy dysregulation, a reasonable order is to build regulation skills, process the memories with a trauma-focused method, then make meaning and plan for setbacks. Some of the regulation work can start at home, as a supplement to therapy rather than a substitute; our guide to somatic reset techniques you can do at home covers several. The order is a plan, not a rule. People move back and forth, and Herman said as much in 1992.
Measurement keeps sequencing honest. In a 2018 meta-analysis of 24 studies, feeding regular progress questionnaires back to therapists reduced deterioration and nearly doubled rates of clinically meaningful change among clients who were predicted to do poorly.48 If the scores have not moved after a fair trial, the plan should change, whether that means a different method, a different phase or a different therapist.
Four questions help you decide where to start. Where does the problem show up: in beliefs, in your body’s automatic reactions, or in the shape of your life? What is your natural tendency, toward analysis or toward feeling? What have you already tried, and what happened? And how much intensity can you tolerate right now?
What this looks like in therapy
The first sessions should be an assessment, not a sales pitch for one method. Expect a history, questions about what you have tried and what helped or did not, standard questionnaires for symptoms such as PTSD, depression and dissociation, and a check on safety. Then the options should be laid out plainly, including approaches the therapist does not provide. If cognitive processing therapy or prolonged exposure is the better fit for you, a referral is part of good care.
The sessions themselves feel different by family. A CBT session has an agenda, a worksheet or a behavioral experiment, and something to practice before next week. An EMDR session holds a memory in mind during sets of eye movements or taps. A Brainspotting session holds the gaze on one point while you track what happens in the body, often with long silences. An IFS session speaks with parts of you, such as the part that keeps you busy or the part that is ashamed. A depth session follows dreams, patterns and the relationship in the room. Most people need more than one of these over time, and a therapist who can move between them is less likely to keep you in the wrong one.
Access shapes these choices as much as clinical judgment. The earlier version of this page said that over 80 percent of psychotherapists do not accept public insurance. We could not verify that figure, and it is cut. The closest solid data concern psychiatrists, not therapists: Tara Bishop and colleagues found that in 2009 and 2010 only 55.3 percent of office-based psychiatrists accepted new patients with private insurance, 54.8 percent accepted Medicare and 43.1 percent accepted Medicaid, far below other physicians, and in the South the private-insurance figure was 43.0 percent.49 How insurance and liability shape what therapists can offer is a problem we take up in psychotherapy ethics when insurance, liability and patient care collide. If you are in crisis, call or text 988.
If you have tried therapy before and something essential seemed to be missing, that history is useful information, not a failure. We see clients in Hoover and by teletherapy across Alabama, and a first conversation can sort out which door makes sense to try next. You can reach us through our contact page.
References
- Ogden, P., Minton, K., & Pain, C. (2006). Trauma and the body: A sensorimotor approach to psychotherapy. W. W. Norton.
- McRae, K., Misra, S., Prasad, A. K., Pereira, S. C., & Gross, J. J. (2012). Bottom-up and top-down emotion generation: Implications for emotion regulation. Social Cognitive and Affective Neuroscience, 7(3), 253–262. https://doi.org/10.1093/scan/nsq103
- Herman, J. L. (1992). Trauma and recovery: The aftermath of violence, from domestic abuse to political terror. Basic Books.
- Beck, A. T. (1963). Thinking and depression: I. Idiosyncratic content and cognitive distortions. Archives of General Psychiatry, 9(4), 324–333. https://doi.org/10.1001/archpsyc.1963.01720160014002
- Hofmann, S. G., Asnaani, A., Vonk, I. J. J., Sawyer, A. T., & Fang, A. (2012). The efficacy of cognitive behavioral therapy: A review of meta-analyses. Cognitive Therapy and Research, 36(5), 427–440. https://doi.org/10.1007/s10608-012-9476-1
- Craske, M. G., Treanor, M., Conway, C. C., Zbozinek, T., & Vervliet, B. (2014). Maximizing exposure therapy: An inhibitory learning approach. Behaviour Research and Therapy, 58, 10–23. https://doi.org/10.1016/j.brat.2014.04.006
- Linehan, M. M., & Wilks, C. R. (2015). The course and evolution of dialectical behavior therapy. American Journal of Psychotherapy, 69(2), 97–110. https://doi.org/10.1176/appi.psychotherapy.2015.69.2.97
- Linehan, M. M. (1993). Cognitive-behavioral treatment of borderline personality disorder. Guilford Press.
- Storebø, O. J., Stoffers-Winterling, J. M., Völlm, B. A., Kongerslev, M. T., Mattivi, J. T., Jørgensen, M. S., Faltinsen, E., Todorovac, A., Sales, C. P., Callesen, H. E., Lieb, K., & Simonsen, E. (2020). Psychological therapies for people with borderline personality disorder. Cochrane Database of Systematic Reviews, 2020(5), Article CD012955. https://doi.org/10.1002/14651858.CD012955.pub2
- Cuijpers, P., van Veen, S. C., Sijbrandij, M., Yoder, W., & Cristea, I. A. (2020). Eye movement desensitization and reprocessing for mental health problems: A systematic review and meta-analysis. Cognitive Behaviour Therapy, 49(3), 165–180. https://doi.org/10.1080/16506073.2019.1703801
- Brom, D., Stokar, Y., Lawi, C., Nuriel-Porat, V., Ziv, Y., Lerner, K., & Ross, G. (2017). Somatic experiencing for posttraumatic stress disorder: A randomized controlled outcome study. Journal of Traumatic Stress, 30(3), 304–312. https://doi.org/10.1002/jts.22189
- Kuhfuß, M., Maldei, T., Hetmanek, A., & Baumann, N. (2021). Somatic experiencing – effectiveness and key factors of a body-oriented trauma therapy: A scoping literature review. European Journal of Psychotraumatology, 12(1), Article 1929023. https://doi.org/10.1080/20008198.2021.1929023
- Corrigan, F., & Grand, D. (2013). Brainspotting: Recruiting the midbrain for accessing and healing sensorimotor memories of traumatic activation. Medical Hypotheses, 80(6), 759–766. https://doi.org/10.1016/j.mehy.2013.03.005
- D’Antoni, F., Matiz, A., Fabbro, F., & Crescentini, C. (2022). Psychotherapeutic techniques for distressing memories: A comparative study between EMDR, brainspotting, and body scan meditation. International Journal of Environmental Research and Public Health, 19(3), Article 1142. https://doi.org/10.3390/ijerph19031142
- Hodgdon, H. B., Anderson, F. G., Southwell, E., Hrubec, W., & Schwartz, R. (2022). Internal family systems (IFS) therapy for posttraumatic stress disorder (PTSD) among survivors of multiple childhood trauma: A pilot effectiveness study. Journal of Aggression, Maltreatment & Trauma, 31(1), 22–43. https://doi.org/10.1080/10926771.2021.2013375
- Shedler, J. (2010). The efficacy of psychodynamic psychotherapy. American Psychologist, 65(2), 98–109. https://doi.org/10.1037/a0018378
- Wampold, B. E., Mondin, G. W., Moody, M., Stich, F., Benson, K., & Ahn, H. (1997). A meta-analysis of outcome studies comparing bona fide psychotherapies: Empirically, “all must have prizes.” Psychological Bulletin, 122(3), 203–215. https://doi.org/10.1037/0033-2909.122.3.203
- Flückiger, C., Del Re, A. C., Wampold, B. E., & Horvath, A. O. (2018). The alliance in adult psychotherapy: A meta-analytic synthesis. Psychotherapy, 55(4), 316–340. https://doi.org/10.1037/pst0000172
- Swift, J. K., Callahan, J. L., Cooper, M., & Parkin, S. R. (2018). The impact of accommodating client preference in psychotherapy: A meta-analysis. Journal of Clinical Psychology, 74(11), 1924–1937. https://doi.org/10.1002/jclp.22680
- Westen, D., Novotny, C. M., & Thompson-Brenner, H. (2004). The empirical status of empirically supported psychotherapies: Assumptions, findings, and reporting in controlled clinical trials. Psychological Bulletin, 130(4), 631–663. https://doi.org/10.1037/0033-2909.130.4.631
- Beebe, J. (2016). Energies and patterns in psychological type: The reservoir of consciousness. Routledge.
- Quenk, N. L. (2002). Was that really me? How everyday stress brings out our hidden personality. Davies-Black.
- Pittenger, D. J. (2005). Cautionary comments regarding the Myers-Briggs Type Indicator. Consulting Psychology Journal: Practice and Research, 57(3), 210–221. https://doi.org/10.1037/1065-9293.57.3.210
- Menon, V. (2011). Large-scale brain networks and psychopathology: A unifying triple network model. Trends in Cognitive Sciences, 15(10), 483–506. https://doi.org/10.1016/j.tics.2011.08.003
- Raichle, M. E., MacLeod, A. M., Snyder, A. Z., Powers, W. J., Gusnard, D. A., & Shulman, G. L. (2001). A default mode of brain function. Proceedings of the National Academy of Sciences, 98(2), 676–682. https://doi.org/10.1073/pnas.98.2.676
- Uddin, L. Q. (2015). Salience processing and insular cortical function and dysfunction. Nature Reviews Neuroscience, 16(1), 55–61. https://doi.org/10.1038/nrn3857
- Fox, M. D., Snyder, A. Z., Vincent, J. L., Corbetta, M., Van Essen, D. C., & Raichle, M. E. (2005). The human brain is intrinsically organized into dynamic, anticorrelated functional networks. Proceedings of the National Academy of Sciences, 102(27), 9673–9678. https://doi.org/10.1073/pnas.0504136102
- Murphy, K., Birn, R. M., Handwerker, D. A., Jones, T. B., & Bandettini, P. A. (2009). The impact of global signal regression on resting state correlations: Are anti-correlated networks introduced? NeuroImage, 44(3), 893–905. https://doi.org/10.1016/j.neuroimage.2008.09.036
- Craig, A. D. (2009). How do you feel — now? The anterior insula and human awareness. Nature Reviews Neuroscience, 10(1), 59–70. https://doi.org/10.1038/nrn2555
- Lieberman, M. D., Eisenberger, N. I., Crockett, M. J., Tom, S. M., Pfeifer, J. H., & Way, B. M. (2007). Putting feelings into words: Affect labeling disrupts amygdala activity in response to affective stimuli. Psychological Science, 18(5), 421–428. https://doi.org/10.1111/j.1467-9280.2007.01916.x
- van der Kolk, B. A. (2014). The body keeps the score: Brain, mind, and body in the healing of trauma. Viking.
- Squire, L. R. (2004). Memory systems of the brain: A brief history and current perspective. Neurobiology of Learning and Memory, 82(3), 171–177. https://doi.org/10.1016/j.nlm.2004.06.005
- Brewin, C. R., Gregory, J. D., Lipton, M., & Burgess, N. (2010). Intrusive images in psychological disorders: Characteristics, neural mechanisms, and treatment implications. Psychological Review, 117(1), 210–232. https://doi.org/10.1037/a0018113
- Hamilton, J. P., Farmer, M., Fogelman, P., & Gotlib, I. H. (2015). Depressive rumination, the default-mode network, and the dark matter of clinical neuroscience. Biological Psychiatry, 78(4), 224–230. https://doi.org/10.1016/j.biopsych.2015.02.020
- Guideline Development Panel for the Treatment of PTSD in Adults, American Psychological Association. (2019). Summary of the clinical practice guideline for the treatment of posttraumatic stress disorder (PTSD) in adults. American Psychologist, 74(5), 596–607. https://doi.org/10.1037/amp0000473
- Schnurr, P. P., Hamblen, J. L., Wolf, J., Coller, R., Collie, C., Fuller, M. A., Holtzheimer, P. E., Kelly, U., Lang, A. J., McGraw, K., Morganstein, J. C., Norman, S. B., Papke, K., Petrakis, I., Riggs, D., Sall, J. A., Shiner, B., Wiechers, I., & Kelber, M. S. (2024). The management of posttraumatic stress disorder and acute stress disorder: Synopsis of the 2023 U.S. Department of Veterans Affairs and U.S. Department of Defense clinical practice guideline. Annals of Internal Medicine, 177(3), 363–374. https://doi.org/10.7326/M23-2757
- Bisson, J. I., & Olff, M. (2021). Prevention and treatment of PTSD: The current evidence base. European Journal of Psychotraumatology, 12(1), Article 1824381. https://doi.org/10.1080/20008198.2020.1824381
- Bisson, J. I., van Gelderen, M., Roberts, N. P., & Lewis, C. (2020). Non-pharmacological and non-psychological approaches to the treatment of PTSD: Results of a systematic review and meta-analyses. European Journal of Psychotraumatology, 11(1), Article 1795361. https://doi.org/10.1080/20008198.2020.1795361
- American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.). American Psychiatric Association Publishing. https://doi.org/10.1176/appi.books.9780890425787
- Lanius, R. A., Vermetten, E., Loewenstein, R. J., Brand, B., Schmahl, C., Bremner, J. D., & Spiegel, D. (2010). Emotion modulation in PTSD: Clinical and neurobiological evidence for a dissociative subtype. American Journal of Psychiatry, 167(6), 640–647. https://doi.org/10.1176/appi.ajp.2009.09081168
- Etkin, A., & Wager, T. D. (2007). Functional neuroimaging of anxiety: A meta-analysis of emotional processing in PTSD, social anxiety disorder, and specific phobia. American Journal of Psychiatry, 164(10), 1476–1488. https://doi.org/10.1176/appi.ajp.2007.07030504
- Hoeboer, C. M., De Kleine, R. A., Molendijk, M. L., Schoorl, M., Oprel, D. A. C., Mouthaan, J., Van der Does, W., & Van Minnen, A. (2020). Impact of dissociation on the effectiveness of psychotherapy for post-traumatic stress disorder: Meta-analysis. BJPsych Open, 6(3), Article e53. https://doi.org/10.1192/bjo.2020.30
- Cloitre, M., Courtois, C. A., Charuvastra, A., Carapezza, R., Stolbach, B. C., & Green, B. L. (2011). Treatment of complex PTSD: Results of the ISTSS expert clinician survey on best practices. Journal of Traumatic Stress, 24(6), 615–627. https://doi.org/10.1002/jts.20697
- De Jongh, A., Resick, P. A., Zoellner, L. A., van Minnen, A., Lee, C. W., Monson, C. M., Foa, E. B., Wheeler, K., ten Broeke, E., Feeny, N., Rauch, S. A., Chard, K. M., Mueser, K. T., Sloan, D. M., van der Gaag, M., Rothbaum, B. O., Neuner, F., de Roos, C., Hehenkamp, L. M., … Bicanic, I. A. (2016). Critical analysis of the current treatment guidelines for complex PTSD in adults. Depression and Anxiety, 33(5), 359–369. https://doi.org/10.1002/da.22469
- Ekers, D., Webster, L., Van Straten, A., Cuijpers, P., Richards, D., & Gilbody, S. (2014). Behavioural activation for depression; an update of meta-analysis of effectiveness and sub group analysis. PLoS ONE, 9(6), Article e100100. https://doi.org/10.1371/journal.pone.0100100
- Richards, D. A., Ekers, D., McMillan, D., Taylor, R. S., Byford, S., Warren, F. C., Barrett, B., Farrand, P. A., Gilbody, S., Kuyken, W., O’Mahen, H., Watkins, E. R., Wright, K. A., Hollon, S. D., Reed, N., Rhodes, S., Fletcher, E., & Finning, K. (2016). Cost and outcome of behavioural activation versus cognitive behavioural therapy for depression (COBRA): A randomised, controlled, non-inferiority trial. The Lancet, 388(10047), 871–880. https://doi.org/10.1016/S0140-6736(16)31140-0
- Watkins, E. R., Mullan, E., Wingrove, J., Rimes, K., Steiner, H., Bathurst, N., Eastman, R., & Scott, J. (2011). Rumination-focused cognitive-behavioural therapy for residual depression: Phase II randomised controlled trial. British Journal of Psychiatry, 199(4), 317–322. https://doi.org/10.1192/bjp.bp.110.090282
- Lambert, M. J., Whipple, J. L., & Kleinstäuber, M. (2018). Collecting and delivering progress feedback: A meta-analysis of routine outcome monitoring. Psychotherapy, 55(4), 520–537. https://doi.org/10.1037/pst0000167
- Bishop, T. F., Press, M. J., Keyhani, S., & Pincus, H. A. (2014). Acceptance of insurance by psychiatrists and the implications for access to mental health care. JAMA Psychiatry, 71(2), 176–181. https://doi.org/10.1001/jamapsychiatry.2013.2862
























0 Comments